What the Anion Gap Measures
The anion gap is a helpful way to look at electrolytes and detect subtle shifts in acid-base balance. It reflects the difference between measured cations and measured anions in the blood, mainly using sodium, chloride, and bicarbonate. In practical terms, it helps clinicians spot whether there are extra unmeasured anions contributing to a metabolic disturbance.
The concept is important because routine serum electrolytes do not capture every charged particle in the bloodstream. The anion gap therefore acts as a diagnostic tool for detecting electrolyte abnormalities and narrowing the differential diagnosis in acid-base disorders. A normal or elevated value can suggest quite different processes, so understanding the pattern matters as much as the number itself.
In many cases, the anion gap provides a fast view of how the body’s buffer system is responding to illness. When acids accumulate, the body may consume bicarbonate and alter the relationship among sodium, chloride, and other ions. That is why the anion gap is often reviewed alongside other lab results during clinical interpretation.
How to Calculate the Anion Gap
The basic anion gap formula is:
anion gap = sodium - (chloride https://anion-gap-chart192.urbanvellum.com/posts/using-an-anion-gap-calculator-to-understand-lab-results + bicarbonate)Some providers also include potassium in the equation, though many everyday calculations omit it because potassium adds relatively little to the final number. A common version that includes potassium is:
anion gap = sodium + potassium - (chloride + bicarbonate)The numbers used come from a serum chemistry panel, which generally reports sodium, chloride, bicarbonate, and sometimes potassium. Because the result depends on the quality of those measurements, the calculation is only as reliable as the original sample and lab methods.
Grasping the formula helps with lab interpretation. A low bicarbonate level can raise concern for metabolic acidosis, while higher chloride may indicate a compensatory pattern or a certain acid-base process. The anion gap does not replace full diagnostic review, but it assists with the first step of diagnostic evaluation.
Using an Anion Gap Calculator
An Anion Gap Calculator automates the formula and reduces manual error when checking lab values. It is especially useful when multiple results need to be interpreted promptly, such as in urgent care settings, emergency assessment, or inpatient monitoring. By entering sodium, chloride, bicarbonate, and sometimes potassium, the calculator returns the anion gap and helps interpret the pattern.
Most calculator outputs should be compared with the lab’s reference range, since the exact normal interval can vary by analyzer and institution. A value that appears borderline in one system may be normal in another. That is why the same number should always be interpreted in context rather than in isolation.
Used correctly, the calculator supports recognition of electrolyte imbalance and helps guide the next clinical step. It can flag whether a patient may have a high-gap process, a normal-gap process, or a mixed disorder. In other words, it is a starting point for clinical interpretation, not the final answer.
Normal Anion Gap vs Increased Anion Gap
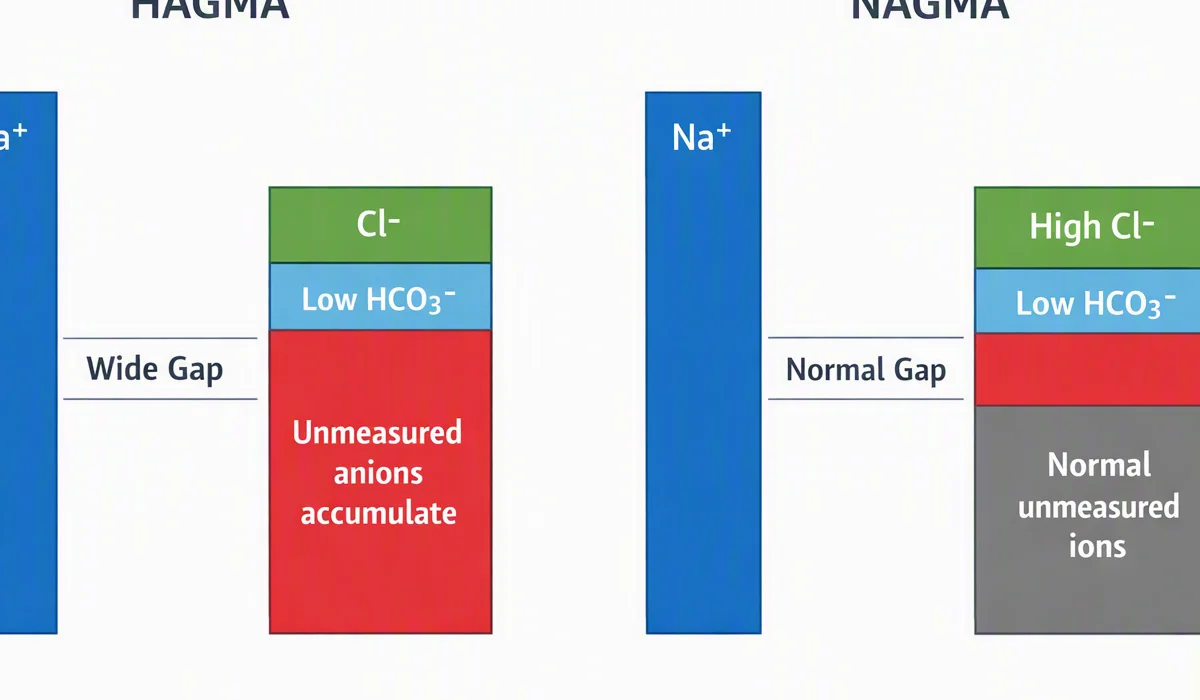
Typical anion gap metabolic acidosis and elevated anion gap metabolic acidosis are two major patterns within metabolic acidosis. Both feature a drop in bicarbonate, but the way chloride and unmeasured acids change is distinct. Spotting the pattern is important because it narrows the source of the acid-base disorder.
In standard anion gap metabolic acidosis, bicarbonate is depleted and chloride rises to preserve electrical neutrality. This is often called a hyperchloremic pattern. In high anion gap metabolic acidosis, bicarbonate declines because acids collect, leaving behind excess unmeasured anions that widen the gap.
The distinction matters because it changes the differential diagnosis. A normal gap pattern often points toward digestive or renal bicarbonate loss, while a high gap pattern suggests added acid load or poor removal of acids. The calculator helps identify the direction, but the complete assessment requires symptoms, history, and other labs.
Frequent Sources of Increased Anion Gap
A number of well-known disorders can produce a elevated gap. Lactic acidosis happens when lactate rises, often due to tissue hypoperfusion, severe illness, or impaired oxygen delivery. Ketoacidosis can arise with diabetes, starvation, or alcohol use, leading to increased ketoacids in the blood.
Renal failure is another major reason because the kidneys cannot clear acids effectively. As acid accumulates, bicarbonate is consumed and the anion gap rises. This pattern is often seen alongside other laboratory changes that reflect reduced kidney function.
Toxic alcohols are an important consideration in the right clinical setting. Ingestions such as methanol or ethylene glycol can produce acid metabolites that raise the gap and create serious toxicity. Because these cases can progress rapidly, the anion gap is one piece of a broader emergency diagnostic evaluation.
Causes of Regular Anion Gap Metabolic Acidosis
When the anion gap stays within the normal range despite acidosis, the problem is often related to straightforward bicarbonate loss or impaired acid excretion. Diarrhea is a common cause because gastrointestinal fluid loss removes bicarbonate from the body. The kidneys may respond by conserving chloride, producing a regular-gap pattern.
Renal tubular acidosis is another significant cause. In this condition, the kidneys cannot properly process acid secretion or bicarbonate reabsorption, which leads to hyperchloremic acidosis. The chloride rise offsets the bicarbonate loss, so the anion gap may remain within the usual range.
These causes are often not recognized if only the final number is reviewed. The clinician must consider hydration status, medication use, kidney function, and recent gastrointestinal losses. A calculator can highlight the pattern, but it cannot by itself pinpoint the underlying source of the metabolic disturbance.
Adjusted Anion Gap and Serum Albumin Adjustment
Albumin is a major unmeasured anion in the blood, so it has a strong influence on the calculated value. When albumin is low, the measured anion gap may appear incorrectly normal or only mildly elevated. This is why the corrected anion gap is often used to improve lab interpretation.
Hypoalbuminemia can hide a true high-gap process. In a patient with low serum albumin, the apparent gap may downplay the number of unmeasured anions. Using a correction formula helps account for that loss and gives a better view of acid-base status.
Correcting for albumin is especially valuable in critically ill patients, malnutrition, liver disease, or other conditions where albumin may be reduced. The adjusted result improves clinical interpretation and can uncover a hidden high-gap state that would otherwise be missed. In practice, the corrected value should be viewed alongside the overall clinical picture rather than used alone.
How to Read Results in a Clinical Setting
The anion gap becomes most useful when paired with the remainder of the workup. A blood gas can show whether a patient has acidemia or alkalemia, while the electrolyte panel helps clarify the pattern of sodium, chloride, and bicarbonate changes. Together, these data provide a more complete clinical evaluation.
When a high gap is present, it is often helpful to ask whether the patient also has an elevated osmolar gap. That can indicate toxic alcohol exposure in the right context. When a normal gap is present, the clinician may look for gastrointestinal bicarbonate loss, renal acidification defects, or iatrogenic causes.
Interpretation should also consider symptoms, vital signs, medication history, kidney function, and timing of the abnormality. The anion gap is a risk assessment tool, not a diagnosis by itself. Its real value lies in structuring the next steps in evaluation and deciding how urgently to act.
Limitations and Common Pitfalls
Even a well-constructed calculator can be affected by measurement error or lab artifact. If one electrolyte is inaccurate, the derived anion gap can be misleading. That is why suspicious results should be repeated and reviewed against the broader clinical picture when necessary.
Another issue is the reference interval. Different labs use different methods, so the definition of “normal” may vary. A value that seems abnormal on one report may fall within another lab’s accepted range. This is one reason a calculator should always be paired with local lab standards.

The delta gap is a useful advanced concept when the clinician suspects a mixed disorder. It compares the change in anion gap with the change in bicarbonate and helps detect whether more than one acid-base process is happening at once. This is particularly helpful when the pattern does not fit neatly into a single category.

Frequently Asked Questions
What is an Anion Gap Calculator used for?
An Anion Gap Calculator is used to calculate the anion gap from serum electrolytes and help identify electrolyte abnormalities and acid-base disorders. It helps with the evaluation of metabolic acidosis, helps distinguish between high-gap and normal-gap patterns, and helps with clinical interpretation of lab results.
What is the normal anion gap range?
The anion gap normal range is determined by the laboratory method and the reference range used by that lab. Because measurement techniques differ, the best approach is to compare the result with the local reference interval rather than relying on a single universal cutoff.
Why does low albumin affect the anion gap?
Low albumin reduces the amount of unmeasured anions in the blood, which can make the measured gap appear falsely low or normal. That is why albumin correction and the corrected anion gap are important in patients with hypoalbuminemia.
What conditions cause a high anion gap?
Common causes of a high gap include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. These conditions introduce acids or reduce acid clearance, increasing the concentration of unmeasured anions and producing high anion gap metabolic acidosis.
Can a normal anion gap still be serious?
Yes. A normal gap can still reflect important disease, especially normal anion gap metabolic acidosis from diarrhea or renal tubular acidosis. It may also represent an early or mixed disorder, so the full clinical evaluation and related lab data matter as much as the gap itself.