What the Anion Gap Measures
The anion gap is a practical way to interpret serum electrolytes and gauge whether unmeasured ions may be affecting acid-base balance. An Anion Gap Calculator typically takes into account the major measured blood chemistry values, especially sodium, chloride, and bicarbonate, to help spot patterns that may suggest a metabolic disorder. In many clinical settings, the result is applied as part of an electrolyte panel rather than as a standalone diagnosis.
At its core, the anion gap shows the difference between positively charged and negatively charged components in the blood. Most calculators center on serum sodium, serum chloride, and serum bicarbonate, while some also include potassium. Because potassium contributes less to the calculation in many routine methods, it may be excluded depending on the formula used. The goal is to calculate anion gap values that help clinicians detect hidden acids, unexpected proteins, or measurement issues.
Understanding the normal reference range matters because a value that appears “normal” in one context may be inaccurate in another. The anion gap is especially important when evaluating possible metabolic acidosis, but it also becomes relevant when the patient has a protein abnormality that can alter blood chemistry. That is where clinical correlation becomes crucial.
How Hyperproteinemia Can Change Anion Gap Assessment
Hyperproteinemia indicates that the blood contains a greater-than-normal amount of plasma proteins. This often involves increased globulins, albumin, or abnormal proteins such as paraproteins. Because these proteins carry electrical charge, they can alter the interpretation of the anion gap even when the calculated number itself is unchanged.
Some proteins, especially negatively charged proteins, act as unmeasured anions. When plasma proteins rise, the body’s measured electrolytes may appear to shift in ways that affect the apparent gap. This is one reason a high protein level can complicate acid-base interpretation. A patient may have a result that looks unexpectedly low or normal, even when there is a true underlying acid-base disorder.
Albumin is the most important protein for this type of interpretation because it is a major unmeasured anion. Low albumin can lower the anion gap, but abnormal protein states can also distort the result through shifts in charge balance or by introducing paraproteins. In conditions such as multiple myeloma or monoclonal gammopathy, abnormal immunoglobulins may alter how the anion gap should be interpreted. In these cases, the number from an anion gap calculator should be viewed as part of a larger diagnostic workup.
How an Anion Gap Calculator Operates
An formula for anion gap is usually derived from measured lab values from the patient’s chemistry panel. The most widely used version is:
Anion gap = sodium - (chloride + bicarbonate)
Some methods incorporate potassium as well, but many clinical calculators exclude it for simplicity and consistency. The exact formula used matters because different labs and references may report slightly different normal results.
The calculator uses serum sodium, blood chloride, and blood bicarbonate to estimate the gap between measured cations and measured anions. If the gap is high, it can suggest the presence of unmeasured acids. If it is low, it may signal hypoalbuminemia, hyperproteinemia, measurement interference, or another issue affecting the blood chemistry.
For practical use, the calculator should be paired with a review of the full electrolyte results. A small change in sodium or chloride can alter the result, so the accuracy of the underlying test values matters. The best way to calculate anion gap results is to interpret them in the context of the patient’s symptoms, other test results, and possible sources of error.
Adjusting the Anion Gap in Protein Disorders
Since albumin heavily impacts the anion gap, numerous clinicians use an albumin-corrected anion gap when protein abnormalities are seen. This type of albumin correction helps avoid missing a clinically important gap that is obscured by low protein levels. It can also enhance interpretation when protein patterns are unusual.
A broader protein correction may be applied when abnormal serum proteins such as paraproteins are suspected. While albumin correction is the most established adjustment, some cases of hyperproteinemia require beyond a single correction step. This is especially true when results do not fit the clinical picture or when the reported value falls near the edge of the reference range.
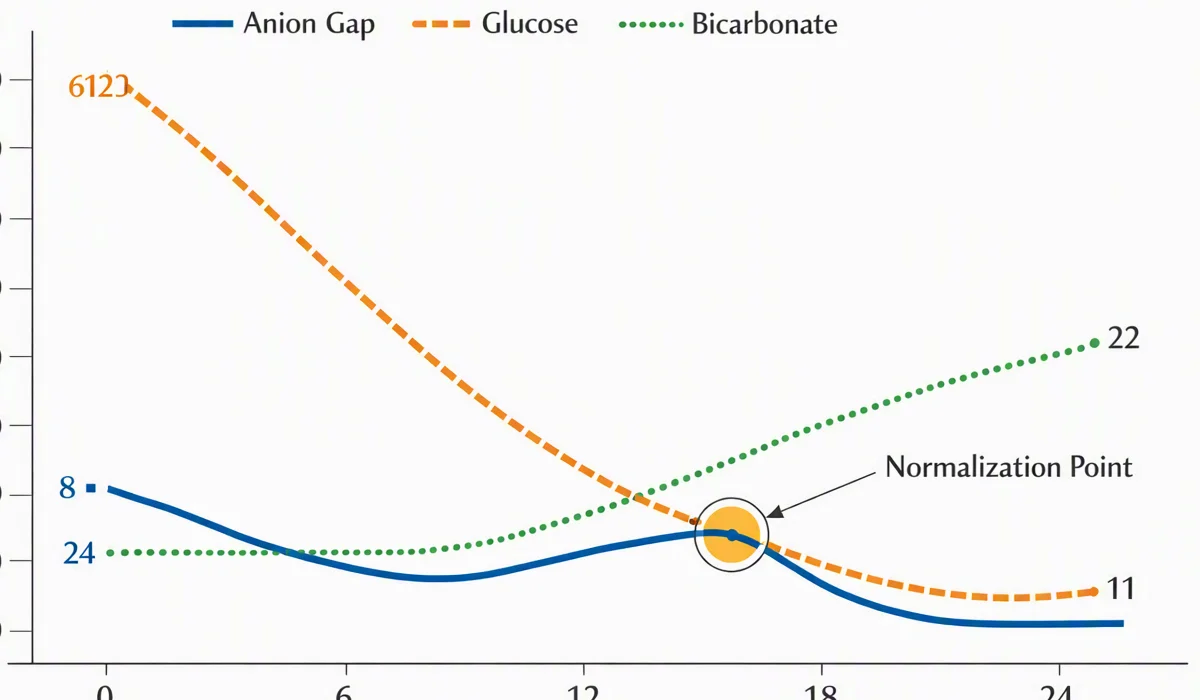
The corrected anion gap is not meant to replace clinical judgment. It is a tool that can sharpen acid-base interpretation and help explain why a result seems disproportionate to the patient’s condition. For example, a patient with low albumin may look as if they have a normal anion gap despite an underlying metabolic acidosis. Conversely, abnormal proteins can make the measured value less straightforward to interpret. In those situations, the corrected anion gap can provide a more useful estimate than the raw number alone.
Typical Causes of Increased or Low Anion Gap
A elevated anion gap is often related to acid retention and is commonly seen in metabolic acidosis. Problems including ketoacidosis, lactic acidosis, toxin exposure, and renal failure are classic causes. However, a high value is not the only abnormal pattern clinicians should identify. A low anion gap can be just as important because it may point to protein changes, lab error, or other hidden issues.
Hypoalbuminemia is one of the most common explanations for a low anion gap because albumin is a major unmeasured negative ion. When albumin falls, the anion gap often falls too. On the other hand, multiple myeloma and other plasma cell disorders can produce paraproteins that disturb the expected pattern. These abnormal proteins may lower the gap or make the result less reliable as a marker of acid-base status.
Lab artifact is another frequent cause of an abnormal result. A falsely low chloride, incorrect sodium value, or sample handling issue can change the calculated result. In some cases, the abnormality is not physiological at all but instead reflects measurement error or interference from the testing method. This is why an unexpected result should always trigger a review of the laboratory values and the testing context.
Working with the Calculator with Clinical Context
The https://privatebin.net/?cca6a66bf8847e6d#Hvya1wWGysimAgfseAAKpDVzeWCALqPQCRPhBzux56dX best application of an Anion Gap Calculator is not mechanical computing but careful clinical interpretation. A result should be interpreted alongside the patient’s symptoms, diagnosis, medications, and other serum proteins. A number alone cannot confirm or rule out an acid-base disorder.
For example, a patient with vomiting, dehydration, or kidney dysfunction may show a varying electrolyte imbalance. Another patient may have a high protein state from chronic inflammation or a plasma cell disorder, which shifts how the result is understood. In each case, the calculator provides a starting point, but the interpretation depends on broader clinical correlation.
It also helps to ask whether the result matches the rest of the data. If the calculated anion gap suggests severe acidosis but the patient looks stable and the bicarbonate is only mildly reduced, the result may need a second look. Likewise, if a patient has known hyperproteinemia and an unexpectedly low gap, the number may reflect altered protein chemistry rather than a true absence of unmeasured acids. This is why many clinicians use the calculator as part of a larger diagnostic workup rather than as a final answer.
Drawbacks of Anion Gap Calculation in Elevated Protein Levels
There are significant limits in diagnosis when using an anion gap calculator in the setting of hyperproteinemia. The calculation assumes that the main measured electrolytes are accurate and that unmeasured ions behave in expected ways. In reality, both assumptions can become unreliable when proteins are abnormal.
One major issue is measurement interference. The electrode-based ion-selective method used in many labs can be affected by atypical sample composition. High protein concentrations may alter the water fraction in plasma and influence how electrolytes are reported. This can produce pseudohyponatremia, in which the reported sodium level is artifactually low even though the physiologic sodium concentration is not truly reduced.
When pseudohyponatremia occurs, the calculated anion gap may be deceptive. A seemingly low sodium can reduce the gap and create a misleading picture of a lab artifact related to acid-base status. In other cases, the issue is not sodium alone but a broader testing error affecting the interpretation of blood chemistry. Because of these limitations, the calculator should never be used in isolation when hyperproteinemia is known or suspected.
When to Review Labs or Evaluate Further
Repeat testing is advisable when the anion gap result does not match the clinical picture or when there is suspicion about a sample or analyzer problem. If the initial result is unexpected, a second chemistry panel can help determine whether the change is real. This is especially helpful when the patient has known or suspected hyperproteinemia, because protein-related effects can vary across assays and collection conditions.
Further evaluation often includes serum protein electrophoresis to look for paraproteins or other abnormal protein patterns. This is an important step when multiple myeloma or monoclonal gammopathy is possible. In addition, checking kidney function can help identify metabolic causes of an abnormal gap, including impaired clearance of acids or related solutes.
Blood gas analysis may be helpful when the bicarbonate result is unclear or when there is concern about true acid-base disturbance. Blood gas testing can clarify whether the patient has a real metabolic acidosis or whether the chemistry panel is affected by a lab issue. If the pattern remains confusing, the clinician may need to check collection method, analyzer type, and the broader diagnostic workup before drawing conclusions.
FAQ About Anion Gap and Hyperproteinemia
How does hyperproteinemia affect the anion gap?
Hyperproteinemia can affect anion gap interpretation because excess plasma proteins, including globulins and paraproteins, can shift the balance of measured and unmeasured ions. The result may look unexpectedly low, normal, or otherwise inconsistent with the patient’s condition. That is why clinical correlation is important when reviewing the anion gap.
Do I need to correct the anion gap for albumin or other proteins?
In many cases, yes. An albumin-corrected anion gap is commonly used because albumin has a strong effect on the calculation. If there is a broader protein abnormality, a more individualized protein correction may be needed. The best approach depends on the available laboratory values and the suspected cause of the abnormal result.
May hyperproteinemia result in a low anion gap?
Yes. A decreased anion gap can be seen in hyperproteinemia, especially when abnormal proteins such as paraproteins are present. It can also be seen with reduced albumin, laboratory artifact, or measurement error. If the result is unexpected, it should be considered in context rather than taken to represent a true physiologic change.
What lab tests may help confirm the cause of an abnormal anion gap?
Helpful tests include a repeat electrolyte panel, SPEP, renal function studies, and sometimes blood gas testing. These tests help clarify whether the issue is related to metabolic acidosis, abnormal blood proteins, or a testing problem involving the ion-selective electrode. They also support a more complete clinical evaluation.
When should an abnormal anion gap be repeated or investigated further?
An abnormal result should be repeated when it does not fit the clinical picture, when there is concern for a sample problem, or when hyperproteinemia may have caused analytical interference. Further investigation is warranted if the abnormality persists, especially if there is concern for multiple myeloma, gammopathy, or another serious metabolic disorder. In those situations, the anion gap calculator is a helpful tool, but not the final step in lab interpretation.