What Is the Anion Gap?
The anion gap is a computed value used in a blood test to assess the levels of electrolytes in the body. It is typically derived from the main measured ions in a serum chemistry panel: sodium, chloride, and bicarbonate. Because not every charged particle is directly measured, the anion gap helps estimate the difference between measured cations and unmeasured anions.
In simple terms, the anion gap is a useful diagnostic tool for assessing acid-base balance. A normal result supports a narrower range of likely causes, while a low anion gap or high anion gap can point toward different types of acid-base disorder. Clinicians often rely on an electrolyte panel or broader serum chemistry to calculate it as part of a metabolic evaluation.
The most common formula is:
Anion gap = Sodium - (Chloride + Bicarbonate)
Because the result depends heavily on the sodium concentration, any condition that changes sodium can change the calculation. That is why sodium, chloride, and bicarbonate level are key to understanding the result.
What Is Hyponatremia?
Hyponatremia refers to a reduced serum sodium level. This is one of the most frequent electrolyte abnormalities encountered in medical care and usually reflects an imbalance in water balance rather than a genuine loss of sodium alone. In numerous cases, the body has excess water relative to sodium, which reduces the measured concentration.
To understand hyponatremia, clinicians also consider osmolality, which shows the concentration of dissolved particles in blood. The combination of serum sodium and osmolality helps clarify whether the sodium abnormality is due to excess water, true sodium loss, or some other mechanism. This is relevant because a low sodium value may be part of a broader electrolyte imbalance or a separate issue that does not directly change the anion gap.
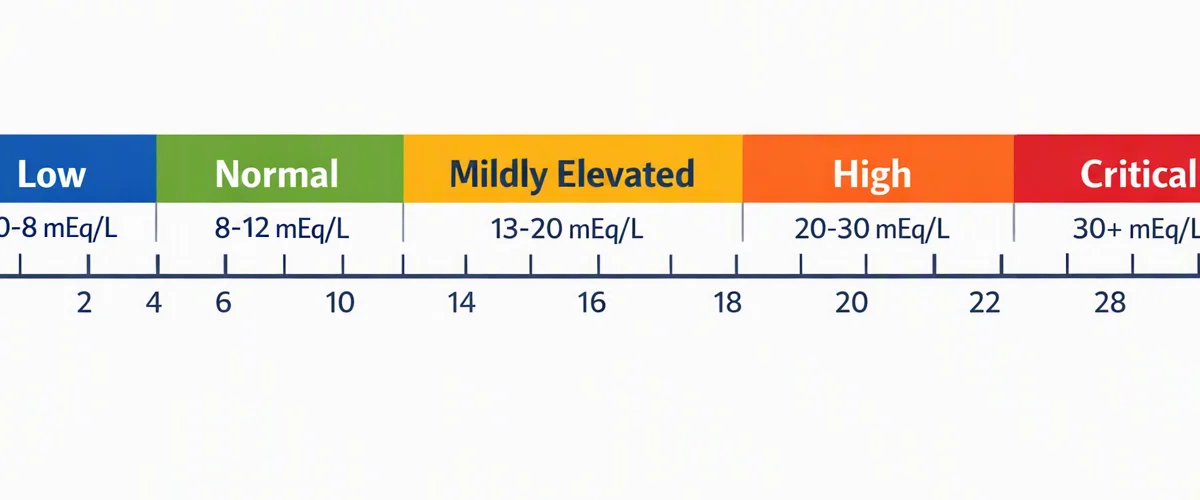
Hyponatremia can be related to many different conditions, including volume changes, hormonal problems, medications, and severe illness. The key point is that the low sodium itself does not automatically mean there is an acid-base disorder. It may be present with one, but the association is not guaranteed.
Can Hyponatremia Alter the Anion Gap?
Indeed, hyponatremia can influence the anion gap because sodium is included in the calculation. If the sodium value drops while chloride and bicarbonate remain stable, the calculated gap may decrease. However, the effect depends on the broader pattern of lab interpretation and not just the sodium number alone.
Using an anion gap calculator can help illustrate how changes in serum sodium influence the result. However, a low sodium level does not always create a truly abnormal gap in a clinically meaningful way. In some cases, the value changes on paper because of the math, while the underlying acid-base status remains unchanged.
For this reason, the anion gap should never be interpreted in isolation. A person may have low sodium from a dilutional process, yet the gap may still be normal after considering the rest of the serum electrolytes. In other cases, a low sodium value may accompany disorders that also lower bicarbonate or shift chloride, leading to a more important change in the gap.
Practical clinical interpretation depends on the full pattern of laboratory values, symptoms, and the suspected diagnosis. The anion gap is an important clue, not the final answer.
In What Way Sodium Values Shape the Computation
The anion gap formula is directly influenced by sodium concentration because sodium is the leading figure in the calculation. When sodium decreases, the numerical gap frequently declines too, assuming chloride and bicarbonate are kept similar. This is a straightforward math effect, but the body’s chemistry is considerably more complex than the formula alone suggests.
Bicarbonate and chloride shift can change the result in different directions. For example, if bicarbonate is low because of metabolic acidosis, the anion gap may increase if the fall in bicarbonate is not matched by a matching increase in chloride. On the other hand, if chloride rises to compensate, the gap may appear normal even though an acid-base problem is present.
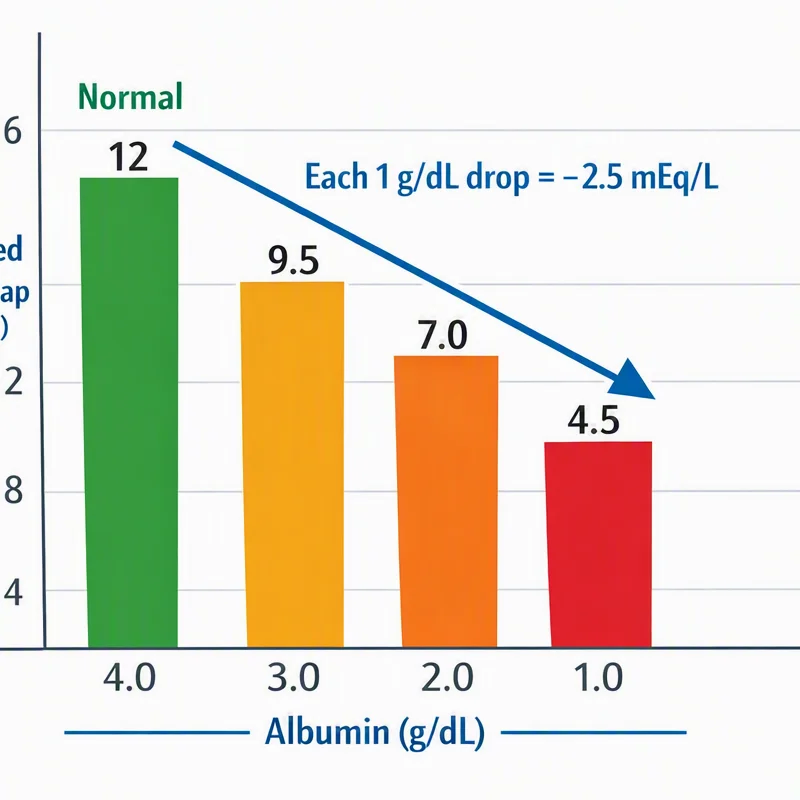
Albumin also plays a role because it is a major unmeasured anion. Lower albumin decreases the anion gap even when the sodium level is stable. So in a patient with hyponatremia, a low gap may reflect both the sodium change and the effect of albumin. This is why a simple calculation can be misleading without considering the rest of the blood chemistry.
In practice, the lab math works best when viewed as part of the full acid-base balance picture. Sodium does affect the number, but it is only one component of the overall interpretation.
When a Low Anion Gap Can Appear
A reduced anion gap is uncommon than a high one, and it often needs careful review. One major cause is hypoalbuminemia, since albumin is a important unmeasured anion. When albumin drops, the gap often drops too, even without a major change https://anion-gap-tool752.lowescouponn.com/what-is-the-link-between-anion-gap-and-bicarbonate in the underlying acid-base state.
Laboratory error is another important possibility. Mistakes in specimen handling, measurement, or reporting can create a falsely low result. If the number does not fit the clinical picture, repeat testing is often necessary before drawing conclusions.
Paraproteinemia can also lower the anion gap. Abnormal proteins may behave as unmeasured cations or alter the electrochemical balance in ways that lower the calculated gap. This is especially relevant when the patient has other findings that suggest a plasma cell disorder.
In some cases, unmeasured cations such as lithium or marked increases in other positively charged substances can decrease the calculated gap. That is why a low result should prompt review of medications, the overall electrolyte panel, and the broader clinical context.
Correcting the Anion Gap
As albumin greatly influences the calculation, clinicians often use an albumin adjustment to determine a more accurate adjusted anion gap. This adjustment assists compensate for the fact that low albumin can mask an elevated gap or make a normal gap appear low.
The reference range for the anion gap varies slightly by laboratory method, so interpretation should always use the range reported with the patient’s test values. A value that looks low in one setting may fall within another lab’s expected range. Method differences matter, especially when comparing results across systems.
Correcting for albumin is especially useful when evaluating possible acidic imbalance. For example, a patient with low albumin and a “normal” gap may still have an elevated corrected gap that more accurately reflects hidden acid accumulation. In that situation, the correction can change the direction of the clinical interpretation.
The goal is not to replace judgment with a formula, but to improve it. A corrected value gives a better estimate of the true acid-base picture and helps identify whether the apparent abnormality is driven by albumin, sodium, chloride, bicarbonate, or a combination of factors.
Using an Anion Gap Calculator
An anion gap calculator is helpful because it rapidly combines the main input values from serum electrolytes. By providing sodium, chloride, and bicarbonate, the calculator gives the calculated gap and often helps check that value with the expected reference range. This is especially useful when examining complex clinical interpretation scenarios.
For patients with hyponatremia, the calculator can show whether the low sodium concentration is likely to have a major effect on the gap. It can also help reveal whether the result is better explained by hypoalbuminemia, a hidden high anion gap, or another abnormality in the lab pattern. In that sense, the calculator is a reliable diagnostic tool for bedside decision-making.
When working with the calculator, make sure the values come from the same specimen and same blood test. Mixed or delayed results can distort the calculation. A careful review of serum chemistry results, along with the patient’s symptoms and history, improves accuracy more than the number alone.
The best use of an anion gap calculator is not just to produce a number, but to support a thoughtful interpretation of the overall metabolic picture.
What Other Tests Should Be Checked?
When the anion gap is out of range, other tests often help clarify the cause. A blood gas can show pH and confirm whether there is an acid-base disorder. It also helps determine whether the patient has acidic blood, alkalemia, or a mixed disturbance.
Serum bicarbonate should be reviewed carefully because it is directly part of the calculation and a major clue to metabolic acidosis. If bicarbonate is low, the clinician should think about causes such as lactic acidosis, ketoacidosis, renal impairment, or toxin exposure.
Lactate is important when evaluating an elevated gap, especially if poor perfusion, infection, or tissue hypoxia is possible. Elevated lactate suggests accumulation of unmeasured acids and can explain a meaningful shift in the gap.
Ketones should also be checked when the clinical setting suggests ketoacidosis, starvation, or severe insulin deficiency. Ketone accumulation increases unmeasured anions and can significantly raise the anion gap. In a patient with hyponatremia, these additional tests help separate a true acid-base problem from a simple sodium imbalance.
Other data may include kidney function, medication review, and assessment for toxin exposure. Together, these help determine whether the abnormal value reflects a transient laboratory issue or a real metabolic problem.
FAQ
Can hyponatremia lower the anion gap?
Yes. Because sodium is part of the anion gap formula, hyponatremia can lower the calculated anion gap. However, the size of the effect depends on the full pattern of chloride, bicarbonate, and albumin. A low sodium value does not always mean the gap is clinically important.
Does a low sodium level always mean a low anion gap?
No, it does not. A low serum sodium does not automatically produce a low gap. The final result depends on the balance of electrolytes, including chloride and bicarbonate, as well as factors like hypoalbuminemia and lab method. Many cases of hyponatremia have a normal anion gap.
How can you adjust the anion gap for low albumin?
You use an albumin correction to determine the corrected anion gap. Since albumin is a key unmeasured anion, low albumin can make the gap seem smaller than it really is. Correcting for albumin improves clinical interpretation, especially when evaluating possible metabolic acidosis.
When ought a low anion gap be repeated or confirmed?
A low gap should be repeated when the result does not fit the patient’s condition or when lab error is possible. Confirmation is also reasonable if the value is unexpected, if the specimen quality is uncertain, or if there is concern for paraproteinemia or unmeasured cations. Repeating the test can help differentiate a real abnormality from a spurious one.
What other tests help interpret an abnormal anion gap?
Helpful tests include a blood gas, serum bicarbonate, lactate, and ketones. These studies help identify whether the abnormality is part of an acid-base disorder, such as metabolic acidosis, or whether it is more related to sodium changes, albumin changes, or another electrolyte imbalance.